
Commonly referred to as male pattern baldness (MPB), it is the most common cause of hair loss in men, accounting for 95% of cases. It affects up to 80% of men at some point and can start as early as the early to late teens.
The prevalence of male pattern baldness in the United States is extensive, affecting approximately 50 million men in the population. Most studies suggest that the incidence increases steadily with age, and without treatment, hair density (fullness) decreases by approximately 6% per year.
A common misconception is that hair thinning and baldness are simply a result of aging. While hair can naturally thin mildly as we age, significant hairline recession or noticeable hair loss that leads to scalp visibility is typically a sign of androgenetic alopecia.
How Common Is Hair Loss? The Numbers May Surprise You
Male pattern hair loss is incredibly common—and the risk increases with age.
- 20s: About 1 in 5 men
- 30s: About 1 in 3 men
- 40s: About 2 in 5 men
- 50s: About 1 in 2 men
- 70s: Up to 4 in 5 men
The condition typically follows a predictable pattern, characterized by a receding hairline, thinning crown, or both. Some men lose their hair quickly, while others experience gradual hair loss over several decades.
The Science Behind Pattern Hair Loss
If you’ve been researching hair loss online, you’ve probably heard the same explanation over and over:
“DHT causes hair loss. Block DHT with finasteride, add minoxidil, and you’re done.”
While there’s some truth to that, it’s only part of the story.
Modern research has transformed our understanding of androgenetic alopecia (male and female pattern hair loss). We now know that it isn’t caused by just one hormone or one gene. Instead, it’s the result of many biological processes working together over years or even decades.1,2
Think of your hair follicles like a thriving garden.
Many people believe DHT is the only weed causing the problem, so they assume pulling that one weed should solve everything. But healthy gardens depend on much more than removing weeds. They need healthy soil, strong roots, enough sunlight, proper watering, and protection from disease. Hair follicles work the same way. DHT is one important factor, but healthy hair also depends on your genetics, growth signals, stem cells, scalp health, blood supply, inflammation, hormones, nutrition, and overall health. If several of these systems aren’t working properly, simply lowering DHT may help—but it may not be enough to restore the healthiest possible hair.
Understanding this helps explain why some people experience incredible results with medication, while others continue to lose hair despite doing “everything right.”
There Is No Single “Hair Loss Gene”
One of the biggest misconceptions about pattern hair loss is that you either inherited the “bald gene” or you didn’t.
In reality, there is no single hair loss gene.
Scientists now know that pattern hair loss is polygenic, meaning it is influenced by many different genes inherited from either side of your family, with each gene contributing a small piece of the overall risk.1,2
So far, scientists have identified more than 380 regions of DNA associated with pattern hair loss. Together, these regions contain hundreds of genes that influence when hair loss begins, how quickly it progresses, which areas of the scalp are affected, and how well someone responds to treatment.1,2
This is why:
- Hair loss can skip generations
- Two brothers can lose their hair very differently.
- One identical twin may thin years before the other.
- Some people notice hair loss in their early 20s, while others don’t until their 50s.
Therefore, while hair loss tends to run in families, it does not always do so in a predictable manner. It’s also possible to develop AGA without a strong family history—genes from other chromosomes and subtle environmental influences still play a role.
Your DNA creates a tendency—not a guarantee.
DHT Is the Trigger—Not the Entire Disease
DHT (dihydrotestosterone) is one of the most important hormones involved in pattern hair loss.
It is a byproduct of free testosterone that attacks hair follicles in genetically sensitive individuals.
DHT is a hormone that plays a key role in male development during puberty. It helps form the male genitalia, increases muscle mass, deepens the voice, and stimulates body and facial hair growth.
But in adulthood, DHT’s role shifts—and not in a good way. While it’s no longer essential after puberty, DHT contributes to several issues:
- Hair Loss (Androgenetic Alopecia): DHT shrinks hair follicles over time, leading to thinning and balding.
- Oily Skin and Acne: DHT increases sebum production, which clogs pores and fuels acne breakouts.
- Dandruff and Seborrheic Dermatitis: By promoting excess oil production, DHT can worsen scalp inflammation and flaking.
- Benign Prostatic Hyperplasia (BPH): DHT stimulates the growth of the prostate gland, which can lead to urinary symptoms like urgency, a weak stream, or incomplete emptying in older men.
An enzyme called 5α-reductase converts free testosterone into DHT, which then binds to androgen receptors in genetically susceptible hair follicles. Interestingly, total testosterone levels are generally similar in men with and without androgenetic alopecia (AGA). However, individuals with AGA tend to have higher levels of free testosterone, the active form of the hormone, which contributes to the increased production of DHT.
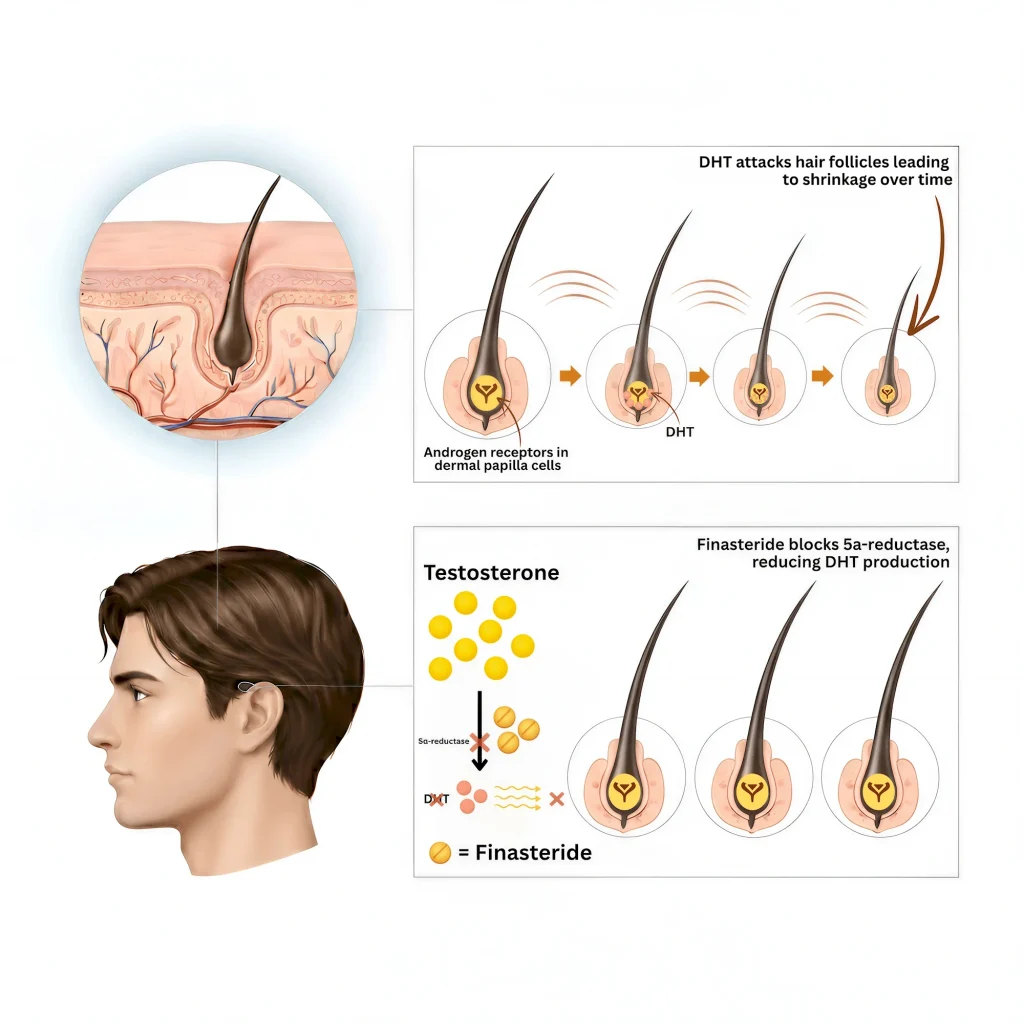
But here’s what many people don’t realize:
DHT doesn’t actually attack or kill the hair follicle.
Instead, DHT acts more like a messenger.
When it binds to androgen receptors inside genetically susceptible hair follicles, it changes how those follicles communicate with surrounding cells.3
Over time, these altered signals alter the hair follicle, causing thick, pigmented hairs (terminal hairs) to gradually be replaced by thin, light-colored, nearly invisible hairs called vellus hairs. This process is known as miniaturization and is the hallmark of male pattern baldness.
This transformation occurs due to a gradual shortening of the hair cycle’s growth phase (the anagen phase) and the lengthening of the resting phase (telogen phase).
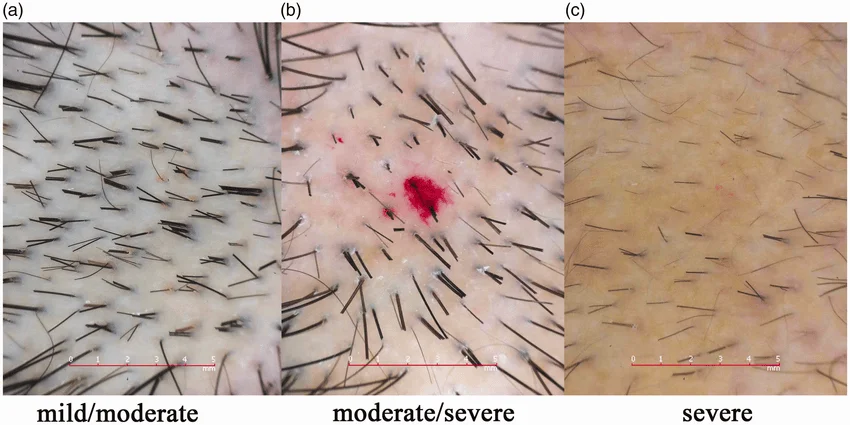
Trichoscopy shows variation in hair shaft diameters, more miniaturized/vellus hairs, peripilar halos, and reduced follicular density, which together confirm patterned hair thinning.
The hair follicles in the hairline, frontal area, and crown are more susceptible because they have higher concentrations of DHT, 5α-reductase enzyme, and androgen receptors, particularly in individuals with AGA. The level of androgen receptors is 1.5 times higher in the frontal scalp compared to the back and sides of the scalp, below the crown. Since hair follicles along the back and sides of the scalp have fewer receptors for the DHT hormone to attach to, hairs from this area are primarily used in hair transplantation procedures.
While this gradual thinning or miniaturization is common, some individuals may also experience periods of increased shedding. The extent and severity of hair loss vary between individuals and are primarily determined by genetic factors.
Eventually, this process can lead to baldness, as the affected hair follicles stop producing visible hair, and the pores where hair normally grows are smoothed over with skin.
In the mid-to-late stages of hair follicle miniaturization, a condition called perifollicular fibrosis—the buildup of scar-like tissue around the hair follicles—is often observed. This can make it harder for treatments for androgenetic alopecia (AGA) to work effectively.
Your Hair Follicles Communicate Through Hundreds of Biological Signals
Hair follicles aren’t simple structures. They’re tiny organs made up of several different cell types that constantly “talk” to one another using chemical messengers.
When these messages stay balanced, hair grows normally.
When they become disrupted, hair follicles gradually begin to fail.
Research has identified several important signaling pathways involved in pattern hair loss.
Wnt/β-Catenin: The “Grow” Signal
One of the most important hair-growth pathways is called Wnt/β-catenin.
Think of it as the follicle’s “Start Growing” switch.
DHT increases a protein called DKK-1, which blocks this pathway and makes it harder for hair follicles to produce healthy, thick hairs.4,5
Prostaglandin D₂: The “Stop Growing” Signal
Researchers have also discovered increased levels of prostaglandin D₂ (PGD₂) in balding scalp.6
This molecule acts almost like a brake pedal, slowing hair growth and making hair follicles less likely to produce thick terminal hairs.
Hair growth depends on maintaining the proper balance between “grow” signals and “stop” signals. Genetic pattern hair loss gradually shifts that balance in the wrong direction.
Your Hair Follicles May Still Be Alive
One of the most exciting discoveries in hair loss research is that many miniaturized follicles aren’t actually dead.
Researchers found that many still contain hair follicle stem cells, but they have difficulty activating the specialized cells needed to produce a healthy hair shaft.7
Imagine a construction site.
The workers are still there.
The tools are still there.
But no one is giving the instructions to start building.
That’s very different from having an empty construction site.
This also explains why early treatment produces the best results. The longer a hair follicle remains miniaturized, the more difficult it becomes to restore normal function.
Your Genes Can Behave Differently
Although you can’t change the DNA you inherited, your genes aren’t always equally active.
Scientists call this epigenetics.
Epigenetics doesn’t change your DNA sequence—it changes how strongly certain genes are expressed.
Researchers have identified differences in androgen receptor regulation between balding areas on top compared to the back and sides of the scalp, where hair often remains permanently resistant to hair loss.8
This helps explain why donor hair used during hair transplantation usually continues growing for decades after being moved.
Scientists continue studying how these genetic “dimmer switches” influence hair loss, but they have not shown that lifestyle changes alone can turn genetic hair loss on or off.
Hair Follicles Can Experience Premature Aging
Every cell in your body produces energy.
As part of that process, cells naturally generate unstable molecules called free radicals.
Normally, your body keeps these molecules under control.
However, research suggests that genetically susceptible hair follicles are more vulnerable to oxidative stress, allowing free radicals to damage important follicle cells over time.9
Think of oxidative stress like rust slowly developing on a car.
The damage isn’t obvious overnight.
But after years of exposure, performance begins to decline.
Scientists believe oxidative stress may accelerate aging within the hair follicle, reducing its ability to support thick, healthy hair.
Low-Grade Inflammation Can Slowly Change the Hair Follicle
Genetic pattern hair loss is not an autoimmune disease, but that doesn’t mean inflammation plays no role.
Researchers have identified low-grade microscopic inflammation, called microinflammation, surrounding affected hair follicles in many patients.10
You usually cannot see or feel this inflammation.
Instead, it quietly alters the environment around the follicle over many years.
Scar Tissue May Gradually Develop Around Hair Follicles
Over time, ongoing hormonal signaling and chronic microinflammation may encourage the body to lay down additional collagen around affected follicles.
This process is called perifollicular fibrosis.11
Think of it like tree roots surrounded by compacted soil.
The tree may still be alive, but the environment makes healthy growth more difficult.
Scientists believe this may be one reason why long-standing hair loss is harder to reverse than early hair loss.
Healthy Hair Needs Healthy Blood Vessel Support
Hair follicles are among the fastest-growing structures in the human body.
That means they require an excellent supply of oxygen and nutrients.
One important growth factor, VEGF (vascular endothelial growth factor), helps maintain the tiny blood vessels surrounding active follicles.12
Interestingly, one way minoxidil appears to work is by increasing VEGF production and supporting these growth signals.
This doesn’t mean hair loss is caused by poor circulation.
Rather, healthy blood vessel support is one important piece of a much larger biological puzzle.
Why Finasteride and Minoxidil Don’t Work the Same for Everyone
Finasteride reduces DHT, while Minoxidil stimulates several growth-promoting pathways.
Both are excellent treatments supported by decades of research.
However, neither medication completely corrects every biological process involved in pattern hair loss.
They don’t directly reverse:
- Your inherited genetics
- Every disrupted signaling pathway
- Oxidative stress
- Stem cell dysfunction
- Tissue remodeling
- Microscopic fibrosis
That’s why one patient may regrow a tremendous amount of hair, another may simply maintain what they have, and another may continue to thin despite appropriate medical treatment.13
This variability isn’t because the medications “failed.” It’s because every person’s biology—and every stage of hair loss—is different.
Do DHT Levels Determine Your Hair’s Fate?
A common assumption is that “if DHT causes hair loss, shouldn’t we test for it?”
It’s a fair question, but the answer isn’t so simple.
Total DHT (blood test)
- Measures the overall amount of DHT in the blood (both bound + free)
- ~98–99% is bound to proteins (mainly SHBG, some albumin)
- Bound DHT isn’t directly active but serves as a reservoir
Free DHT (blood test)
- Measures the small fraction of unbound DHT circulating in your bloodstream
- Tells you how much biologically active DHT is available systemically
- It does not directly reflect how much DHT is acting in a specific tissue, like the scalp
Why Blood DHT Doesn’t Tell the Full Story
- DHT levels in your scalp are what matter, not your blood 14
- You can have “normal” blood DHT but still have high levels in your scalp
- Some people have high DHT and no hair loss — their follicles don’t mind it because they have reduced sensitivity
Scalp DHT (tissue level)
- Refers to the local concentration of DHT inside the scalp/hair follicles
- This is where DHT binds androgen receptors and drives hair follicle miniaturization in androgenetic alopecia
- Scalp levels can be very different from blood levels, since DHT is produced locally in hair follicles by 5-alpha reductase activity
How Scalp DHT Can Be Measured
- Requires a scalp biopsy (removing a small piece of scalp skin)
- The tissue is then analyzed in a research lab for intrafollicular DHT levels
- Sometimes measured in clinical trials studying finasteride/dutasteride but not offered in standard labs
Why It’s Not Done in Practice
- Invasive, uncomfortable, leaves a scar
- Costly and not covered by insurance
- No validated commercial test exists
- Results wouldn’t typically change treatment, since we already know DHT in the scalp drives androgenetic alopecia and we target it with standard medications
What this comes down to is your genetic sensitivity to DHT, and not the amount of DHT you produce. However, if you are sensitive to DHT, the more you make, the more hair loss you may have.
This study supports that conclusion. Researchers compared DHT levels in people with and without hair loss and found that the levels were about the same in both groups. This suggests that simply having more DHT in your system isn’t what causes hair loss. Instead, the key factor seems to be how sensitive your hair follicles are to DHT. Some people’s follicles are genetically more responsive to it, which can trigger hair thinning—even if their hormone levels are completely normal.
Hamilton-Norwood Scale: A Roadmap for Male Hair Loss
The Hamilton-Norwood scale is a tool used to track the stages of male pattern baldness. Think of it as a map that shows how hair loss progresses over time. It’s divided into seven stages, starting with a slight recession of the hairline and ending with extensive balding across the top of the scalp.
Doctors and hair specialists use this scale to understand where someone is in their hair loss journey.

Stage 1
- No significant hair loss
- The hairline appears full with no noticeable recession
Stage 2
- Slight recession at the temples (often called a “mature hairline”)
- Still looks natural, but the corners of the hairline begin to move back
Stage 3
- The first stage that is considered true balding
- Deeper recession at the temples forming an “M” shape
- May also see early thinning at the crown (NW 3V)
Stage 4
- More severe temple recession and a visible bald spot at the crown
- A band of hair along the midscalp still separates the front hairline from the crown
Stage 5
- Hair loss at the front and crown is more significant
- The band of hair along the midscalp becomes thinner and narrower
Stage 6
- The bridge of hair along the midscalp disappears
- The bald areas at the front and crown merge into a larger bald area
- The band of hair along the back and sides of the scalp (“horseshoe pattern”) remains
Stage 7
- Most severe stage of hair loss
- The band of hair along the sides and back becomes much thinner and lower
What Is Retrograde Alopecia?
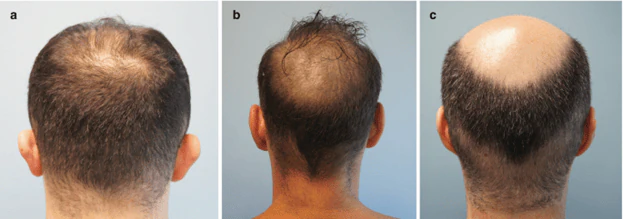
Retrograde alopecia (RA) is a type of hair loss that often co-occurs with hereditary hair loss. It begins at the nape of the neck and progresses upward, affecting areas typically resistant to hair loss. It can also affect the hair along the temples.
- Often seen in advanced stages of hair loss
- It can limit the availability of donor hair for hair transplantation
- It is important to detect early to determine hair transplant candidacy and guide treatment options

Hair Loss Is More Than a Cosmetic Problem
Hair follicles are incredibly sophisticated “mini organs.”
While the old explanation that “DHT causes hair loss” isn’t wrong—it just isn’t the complete story.
Understanding this complexity helps explain why there is no single “magic pill” for hair loss—and why an individualized treatment plan often produces the best long-term results.
The earlier these processes are recognized and treated, the greater the opportunity to preserve existing hair, slow progression, and maximize long-term outcomes.
We believe in treating the entire biology of hair loss, not just one hormone.
That means looking beyond DHT to evaluate factors such as scalp health, hair care products, inflammation, nutrition, vitamin and mineral status, hormonal balance, medication and supplement review, and other medical conditions that may influence hair growth.
A 360-Degree Approach
A proper evaluation includes:
- Hair loss history: timeline and pattern of hair loss
- AI-powered scalp analysis with TrichoLab for precise imaging
- Review of medical & family history
- Review of medications, supplements, diet, hair care products, and practices
- Lifestyle factors (diet, stress, sleep, etc.)
- Comprehensive blood testing
Every detail helps us identify what’s driving your hair loss — so we can target the right treatment.
If you’ve ever walked into a hair loss consultation only to leave feeling rushed or unheard, you’re not alone. Too often, patients describe their experience like this: the doctor glances at their scalp from a few feet away, delivers a quick diagnosis, and recommends a treatment—all within a minute or two.
No deep questions. No hands-on evaluation. No real understanding of what’s going on beneath the surface.
Hair loss isn’t just about evaluating your hair. It’s about understanding your unique biology, taking a 360-degree approach that helps uncover underlying causes and contributing triggers from every angle, leading to more personalized and effective treatment.
At YAKER Hair Restoration + Med Spa, we go deeper, combining medical insight, cutting-edge tools, and a personalized approach to get you real answers.
What If It’s Not Genetic Hair Loss?
Not all hair loss is caused by genetics. When there’s sudden, patchy, or widespread shedding, we dig deeper.
Other causes we consider:
- Telogen effluvium (TE): Triggered by stress, illness, nutritional or hormonal imbalances, and scalp or systemic inflammation
- Diffuse alopecia areata: Autoimmune-related hair loss
- Cicatricial (scarring) alopecia: Inflammation that permanently damages hair follicles
These conditions often overlap, making it difficult to determine what is truly happening. That’s why a thorough evaluation matters.
When men notice thinning hair, it’s often a sign of more than hair issues—it can hint at deeper health changes. Let’s explore the hidden causes—and what you can do about them.
Hair Loss Isn’t Always Just About Hair
What’s Happening Inside: Hidden Health Links to Hair Loss
When most people think of hair loss, they assume it’s only a cosmetic issue. But androgenetic alopecia (AGA)—also known as male pattern baldness—is more than a hair issue. Research shows it can be connected to other health problems that share similar genetic, hormonal, or metabolic roots.
Cardiovascular Disease
Men with AGA—especially early onset—are more likely to develop heart conditions like:
Why the connection?
- Androgen sensitivity genes may affect both hair follicles and blood vessels
- DHT can impair vascular function and increase bad cholesterol
- Chronic inflammation and oxidative stress, common in both AGA and heart disease, damage blood vessels and hair follicles alike
- Men who start balding before age 30 may face a higher risk of serious cardiovascular disease later in life
Metabolic Syndrome
This cluster of conditions includes: 17
- Obesity
- High blood pressure
- Insulin resistance
- Abnormal cholesterol
Men with AGA are more likely to develop metabolic syndrome, which increases heart disease risk.
Why?
Androgen (male hormone) sensitivity, insulin resistance, and low-grade inflammation affect both metabolism and hair loss progression.
Insulin Resistance & Type 2 Diabetes
AGA has been associated with insulin resistance and blood sugar dysregulation. 18,19
These factors:
- Decrease blood flow to the scalp
- Increase DHT activity
- Promote inflammation and follicle damage
This can speed up the miniaturization process in genetically susceptible individuals.
Benign Prostatic Hyperplasia (BPH)
DHT plays a major role in both: 20,21
- AGA, by shrinking hair follicles
- BPH, by enlarging the prostate
Men with AGA may be at a higher risk of developing urinary symptoms due to an enlarged prostate as they age.
Mental & Emotional Health
Hair loss isn’t just physical—it affects how people feel:
- Self-esteem drops as the hairline recedes
- Anxiety or depression is common, especially with early or aggressive AGA
- Body image issues can impact relationships, career confidence, and quality of life
Mental health support is just as important as medical treatment in many cases.
Sleep Disorders
Some studies suggest men with AGA may be more likely to experience disrupted sleep quality 22 or obstructive sleep apnea (OSA). 23
Why?
- Shared traits, such as obesity, metabolic disorders, and inflammation, may be linked to the two
- OSA affects hormone balance and blood flow—both crucial for healthy hair growth
What This Means for You
AGA might start at the scalp—but its reach can go far beyond hair.
If you’re dealing with significant or early-onset hair loss, it’s worth having a broader health check-up.
Ask your provider about:
- Heart health screening
- Metabolic panel (glucose, lipids, insulin)
- Inflammation markers
- Sleep apnea evaluation if you have sleep issues
- Prostate health (if you’re over 40)
Hidden Triggers of Androgenetic Alopecia (AGA)
Testosterone Therapy: A Double-Edged Sword
Testosterone therapy is on the rise—yet many men start it without needing it, or without proper testing or follow-up. Studies show:
- 12% of men who receive testosterone actually need it. 24
- Testosterone is often prescribed without ruling out underlying health issues. 25
- Nearly half aren’t monitored appropriately after starting.
- They are given ultra-high doses unnecessarily to get you hooked and keep coming back
- They are convinced that the cause of all their problems is “low” testosterone
That’s a problem.
Free vs. Total Testosterone: Know the Difference
Total testosterone tells you how much testosterone is circulating in your bloodstream. However, much of that testosterone is bound to proteins and is not biologically active.
Free testosterone is the active form your body uses to regulate libido, muscle growth, mood—and yes, hair loss.
It’s also the form that gets converted into DHT, a major driver of AGA.
This means that a normal or even excellent total testosterone level does not necessarily mean your hormones are balanced. Two men can have the exact same total testosterone level but have very different free testosterone levels depending on how much is bound versus free.
Too many clinics focus on total testosterone levels without ever measuring free testosterone, which is what really matters when it comes to treating low testosterone and minimizing hair loss risk.
How DHT Sensitivity Accelerates Hair Loss
Everyone makes DHT, but not everyone’s hair reacts the same.
- If you’re genetically sensitive, even normal levels of DHT can trigger hair loss
- If you’re not genetically sensitive, you might have high testosterone and still keep your hair
The key isn’t just how much testosterone you have—it’s how your follicles respond to it. That’s why pushing testosterone too high (even for “anti-aging” reasons) can speed up balding in vulnerable patients.
Optimal Testosterone Levels by Age
With the growing popularity of testosterone replacement therapy (TRT), I regularly see men and women seeking help for hair loss concerns. Alarmingly, 90% of these patients have testosterone levels well above the normal range for their age. More than 65% do not have their hormone levels monitored regularly, and 95% fail to test free testosterone.
For men, testosterone levels generally peak at age 30 and gradually decline with age. All testosterone values can vary slightly between laboratories, but here’s a general guide:
| Age | Total Testosterone Range | Avg. Total T | Free Testosterone Range | Avg. Free T |
|---|---|---|---|---|
| 19–29 | 264–916 ng/dL | ~600 ng/dL | 9.3–26.5 ng/dL (93–265 pg/mL) | ~15 ng/dL (150 pg/mL) |
| 30–39 | 264–916 ng/dL | ~600 ng/dL | 8.7–25.1 ng/dL (87–251 pg/mL) | ~14 ng/dL (140 pg/mL) |
| 40–49 | 250–850 ng/dL | ~550 ng/dL | 6.8–21.5 ng/dL (68–215 pg/mL) | ~12 ng/dL (120 pg/mL) |
| 50–59 | 215–850 ng/dL | ~500 ng/dL | 6.1–19.3 ng/dL (61–193 pg/mL) | ~10 ng/dL (100 pg/mL) |
| 60–69 | 196–859 ng/dL | ~450 ng/dL | 5.0–16.7 ng/dL (50–167 pg/mL) | ~9 ng/dL (90 pg/mL) |
| 70+ | 156–819 ng/dL | ~400 ng/dL | 4.5–13.9 ng/dL (45–139 pg/mL) | ~8 ng/dL (80 pg/mL) |
Aim to keep your free testosterone in the average range for your age—not above it. Ensure labs include free testosterone, not just total levels.
Going too high cannot only increase your chances of experiencing more hair loss but also lead to other unwanted side effects.
The Dark Side of High Testosterone: What Every Man Should Know
When testosterone levels climb too high, especially without proper monitoring, it can lead to serious, sometimes irreversible side effects.
Hormone Imbalances
- Estrogen conversion → gynecomastia (male breast enlargement)
- Suppressed natural testosterone → infertility, testicular shrinkage
Heart & Metabolic Risk
- Polycythemia → thickened blood, leading to increased blood clot, heart attack, and stroke risk
- Increased LDL, decreased HDL → heart disease
- Insulin resistance → poor blood sugar control → higher chance of developing type 2 diabetes
Liver & Kidney Strain
- Potential liver toxicity and impaired kidney function
Mood & Behavior
- Aggression, irritability, anxiety, or depression
Skin & Hair
- Oily skin and acne breakouts
- Accelerated hair loss in genetically prone individuals
- Worsening scalp seborrheic dermatitis (due to increased sebum production)
Prostate
- BPH (enlarged prostate) → urinary symptoms
Can Testosterone Trigger Hair Loss—Even with Using Hair Treatments?
Yes—and here’s why.
If you’re using DHT blockers (like finasteride/dutasteride) but still losing hair on testosterone, this might explain it:
Think of it like blood pressure meds—you can’t eat high-sodium foods and expect the pill to work.
Similarly, if you’re increasing DHT with high testosterone, it can overpower the meds trying to reduce it.
Why Hormone Clinics Often Miss the Hair-Loss Connection
When you see a hormone specialist to optimize your testosterone, hair loss may not even come up. That’s because:
Hair Loss Isn’t on Their Radar
Hormone doctors focus on lab numbers—not hair loss history. But if you have the genes for male pattern hair loss, your follicles react more strongly to DHT (a byproduct of free testosterone).
Final Thoughts on Testosterone
If you’re concerned about hair loss while on testosterone therapy:
- Let your hormone specialist know about your hair loss
- Stay within age-appropriate ranges—check your free testosterone range with your hormone specialist to ensure they don’t go too high
- Get your free testosterone checked regularly—not just total testosterone
- Avoid chain clinics that follow a one-size-fits-all approach
- Combine therapy with proper DHT-blocking treatments
Insulin Resistance and Hair Loss
Insulin resistance or diabetes can worsen genetic hair loss by:
- Increasing free testosterone → more DHT conversion
- Reducing blood flow to the scalp → fewer nutrients to the hair follicles
- Promoting inflammation and oxidative stress → damaged hair follicles
The fix: Control blood sugar, improve circulation, reduce inflammation, and address hormone balance.